The 2nd edition of Guide to the Elimination of MRSA Transmission in Hospital Settings by APIC outlines the recommendations for antimicrobial stewardship. According to the Guide, infection preventionists have the responsibility to:
1. Establish timely communication systems to caregivers when MDROs are identified
2. identify MDRO transmission in the acute care setting
3. Recognize MDRO resistance patterns
4. Monitor for and recognize novel resistance
5. Collaborate with laboratory, pharmacy, and other team members to plan and implement effective interventions
In addition, APIC recommends the preparation of annual antibiograms for specific units within a hospital to identify suspected outbreaks within defined areas of the hospital. IPs should also review the following frequently in order to better understand changes in MRDOs' resistance trends:
1. Compliance with infection prevention policies minimizing transmission risks
2. Changes to infection prevention practices
3. Changing resistance patterns within the community
4. Entry of resistant pathogens or new resistant clones into the facility
5. Addition of medical services
6. Changes to patient populations who are at risk for MRSA and MDROs
Monday, January 10, 2011


Friday, January 7, 2011
Thanks, Andrew Wakefield

Yesterday, the British Medical Journal published an analysis by journalist Brian Deer detailing his research into the breathtaking fraud committed by Andrew Wakefield, the first to publish a study linking autism with the MMR vaccine. Wakefield published his fraudulent study in Lancet in 1998, and while it was retracted in February 2010, the damage had already been done. The vaccination rate in the U.K. had dropped from 92% to 78.9%, with the result that not enough children were vaccinated to retain herd immunity, and there were huge measles outbreaks. Now, the anti-vaccine movement has worldwide supporters, despite there being no credible scientific evidence linking vaccines to autism.
Brian Deer initially raised concerns about Wakefield’s Lancet study in 2004, prompting the General Medical Council to conduct one of their longest-ever hearings from 2007-2010. By that time, Wakefield had moved to Austin, Texas, and was working as a founder of Thoughtful House, a center for anti-vaccine activist research. When the recommendation came in February 2010 that his U.K. medical license be stripped, Wakefield resigned from Thoughtful House (though it’s unclear whether he actually resigned willingly or was effectively fired). Three months later, in May, Wakefield’s medical license was, in fact, stripped due to his “serious professional misconduct,” with the ruling calling him “dishonest,” “unethical,” and “callous”.
Deer’s BMJ article goes into the actions taken by Wakefield to willfully distort the truth so he could provide fodder for a lawsuit against vaccine manufacturers. That’s right, two years before the publication of the Lancet study, Wakefield had been recruited as part of an effort to sue vaccine manufacturers. Wakefield’s research, using children who were also claimants in the lawsuit, had been supported to the tune of £55,000 from lawyers. Worse, Wakefield himself was paid over £400,000 over an 8- to 10-year period. Wakefield disclosed none of these conflicts of interest. To this day, he insists that his research was correct and that there was no wrongdoing at all, saying that any evidence against him is merely a result of a conspiracy.
One of Brian Deer’s closing paragraphs deals with the harm caused by Wakefield’s study, and the ensuing anti-vaccine movement in general. “As parents’ confidence slowly returned in Britain, the scare took off around the world, unleashing fear, guilt, and infectious diseases – and fueling suspicion of vaccines in general. In addition to measles outbreaks, other infections are resurgent, with [the] state of California last summer seeing 10 babies dead from whooping cough, the worst outbreak since 1958.” Hopefully anti-vaccine supporters will finally take note.
Deer’s article in the BMJ: http://www.bmj.com/content/342/bmj.c5347.full
A shorter, but still thorough, recap of Deer’s article from Orac at ScienceBlogs: http://scienceblogs.com/insolence/2011/01/piltdown_medicine_andrew_wakefields_scie.php
Tuesday, January 4, 2011
California releases first report on HAIs
Last week California released its first report on hospital acquired infections. The report is the result of a piece of legislation that was passed in 2008, which required all acute care hospitals to report their HAIs to the state.
The State received complete surveillance data from 256 hospitals (66.8% of total). The median hospital-specific BSI rates were:
- 0.026 per 1000 inpatient-days for MRSA
- 0.011 per 1000 inpatient-days for VRE
- 1.10 per 1000 central line days for ICU CLABSI
- 0.74 per 1000 central line days for non-ICU CLABSI
The State acknowledged that there were significant limitations in the data due to variations in how hospitals conduct surveillance and reporting. Some hospitals submitted incomplete data due to lack of resources, others failed to report any data. Among those who submitted data, the submissions had no standard format.
Instead of trying to fix the State reporting system, California is now requiring all hospitals to report to NHSN.
Wednesday, December 29, 2010
How to be a successful IP in the 21st Century?
The article entitled “Expanding infection preventionists’ influence in the 21st Century:
Looking back to move forward” in the December issue of American Journal of Infection
Control (AJIC) describes the three essential skills an IP should possess in order to be
effective in the 21st century.
The article highlights the challenges today’s IPs face in health care organizations as their role expands to issues beyond traditional infection control, such as in antimicrobial stewardship, facility design, patient outcome improvements, and more.
Self-knowledge, strategic relationships, and reciprocity are the three essential skills IPs need to master in order to be effective in their organizations.
Self-knowledge is the ability to understand one’s own strengths and weaknesses and knowing how and when to apply one’s capabilities.
Strategic relationships are those relationships the IPs rely on to make things happen. Few IPs have real power but they do have access to key decision makers. Successful IPs need to learn to build and leverage key relationships to get things done.
Reciprocity is the idea that one must give to receive and is considered by some as themost successful approach to daily decisions because it demonstrates a willingness to becooperative. It is important for an IP not to be perceived as asking for resources and support;
instead, IPs should seek common ground with others, offer assistance and compromise
where appropriate.
The last piece of advice in the article is that “IPs should take every opportunity to reach out, introduce themselves, describe their roles and responsibilities, communicate effectively, and provide information pertinent to those they seek to influence. Such people include administrators, nurses, physicians, patient safety officers, performance improvement teams, colleagues, peers, policy makers, or others.” Only after an IP has proven their value and credibility can she or he begin to fully utilize the above mentioned skills.
Monday, December 27, 2010
What's going to be on your next IP Certification exam?
The Certification Board of Infection Control and Epidemiology, Inc. (CBIC) completed a survey in September of this year to evaluate the current role of infection preventionists (IPs) and to determine which topics to cover in the IP certification examination.
The survey asked practicing IPs to evaluate the 76 tasks that are on the current exam by first deciding whether or not a particular task is necessary for the job and second to rate the task’s significance. A decision rule was then applied to eliminate tasks from the exam based on the survey results. Finally the remaining tasks were grouped into themes or content domain and the number of questions for each content domain was assigned.
Here are the tasks that were removed from the exam:
#14 – Determine methods for monitoring and evaluating antimicrobial use
#25 – Use advanced statistical techniques to describe data
#58 – Prepare and manage the infection prevention and control program budget
#75 – Participate in research activities (e.g. product evaluation, prevalence surveys)
#76 – Conduct research in infection prevention and control either independently or collaboratively
Here are the content domains and the number of questions in each one:
1. Identification of infectious disease process – 18 questions
2. Surveillance and epidemiologic investigation – 38 questions
3. Preventing/controlling the transmission of infectious agents – 39 questions
4. Employee/occupational health – 10 questions
5. Management and communication (leadership) – 16 questions
6. Education and research – 14 questions
Total – 135 questions
Wednesday, December 22, 2010
HAI Case Studies
Dear IPs,
For those of you who do not receive AJIC or have been too busy to read it, I have attached some links that I think are useful. There are three case studies that NHSN and APIC developed. The case studies challenge your skills at determining if a patient has an HAI. You can answer online and then read the correct answers and explanations. You do not have to be a member of APIC to access the sites.
Here are the links to case studies that are currently available. Have fun!
Case 2
Case 3
Monday, December 20, 2010
Hemoglobin gene as a potential screening factor for Staph susceptibility?
The New York Times recently published an interesting article on the research of Dr. Eric P. Skaar at Vanderbilt University. Dr. Skaar began researching Staphylococcus in 2002, a deadly bug that kills about 100,000 Americans each year and is the number one cause of hospital acquired infections.
Dr. Skaar's research focused on learning why some people are more susceptible to Staph than others. Like all organisms, Staph needs iron to survive and it obtains iron by bursting open red blood cells and binding itself to hemoglobins. Because there are genetic variations in hemoglobin, Dr. Skaar suspects that Staph prefers certain hemoglobin over others. His research has already established that Staph prefers human hemoglobin over hemoglobin from other animals such as mice. Dr. Skaar is now focused on identifying those genetic variations in hemoglobin that are most preferred by Staph.
If he is successful, hemoglobin screening may become a routine tool to test a patient's susceptibility to Staph.
Link to New York Times article
Monday, December 13, 2010
Poor nations have higher HAI rates
Researchers from the World Health Organization reviewed over 200 published studies on hospital acquired infections (HAIs) and found that these countries have much higher HAI rates than the U.S. and Europe.
The infection rate in developing countries was 15.5 per 100 patients, compared to 7.1 in Europe and 4.5 in U.S. The difference in intensive care units was even more pronounced - 4.7 per 1,000 patient-days in developing countries compared to 13.6 in the U.S.
According to one of the researchers, Professor Didier Pittet, "There can be a misconception that healthcare-associated infections are not often found in developing countries, simply because their healthcare systems are blitzed with other issues that high-income countries have dealt with or controlled long ago."
This study demonstrated that HAIs are highly prevalent in developing countries. It's reasonable to assume the higher infection rates are leading to longer hospital stays, extra costs, and deaths. According to the study, simple, low cost measures such as better hand hygiene, surveillance, and education could drastically reduce infection rates.
Abstract and link to full article here
Friday, December 10, 2010
“Germ Cops” or “Prophets in the Wilderness”?

Recently, there’s been a story floating around about infection prevention practices at University of Maryland Medical Center. The success that UMMC has had is remarkable, to be sure. What is even more remarkable is the variety of interesting terms journalists use to describe the job of infection prevention. If you Google articles related to the UMMC story, you get labels varying from “Germ cop” to “Germ inspector” to “eagle-eyed hospital worker” and even “prophets in the wilderness.”
In Atul Gawande’s 2007 book Better: A Surgeon’s Notes on Performance, the first chapter highlights the role of the infection preventionist, describing a day-in-the-life of Brigham and Women’s IP Deb Yokoe. Gawande quotes Yokoe as saying “I don’t want to be an infection control cop.” At the 2010 APIC keynote when Gawande repeated the same quote, an auditorium full of IPs applauded the sentiment. Perhaps the Associated Press writers should pick their headlines with more sensitivity, though I understand these labels demonstrate a flare for the sensational.
I will leave it up to individual IPs to describe how they view their job, and how they’d like to be viewed. I do know that IPs want to shed the sometimes adversarial relationship they have with other health care workers, and they want to be seen as partners in providing better quality care.
Wednesday, December 8, 2010
Resistance is useless
Not just a Vogon catchphrase anymore, a new study in Lancet Infectious Diseases has some wondering about the effect of antibiotic resistance in bacteria. I’m actually a little uncomfortable with the way that infectioncontroltoday.com summarized the recently-published article by Lambert et al., titled “Clinical outcomes of healthcare-associated Infections.” Lambert et al. studied almost 120,000 ICU patients over a four-year time span in 10 European countries. Unsurprisingly, they found that patients who acquire a healthcare-associated infection have worse outcomes than those that don’t. However, they go on to say that if the infection acquired is resistant to narrowly-specified antibiotics, the fact of the resistance itself does not make the outcome much worse.
Specifically, the study finds that pneumonia doubles the risk of death and BSIs triple the risk of death, but when the bacteria causing those infections is antibiotic-resistant, there is only a 20% increase in the likelihood of death (results significant just for pneumonia). “Only.”

Now, I understand that 20% is not much when compared with 200%, and that that difference is what generated ICT’s summary title “Resistance Does Not Greatly Impact Mortality in ICU Patients with HAIs,” and that’s a valid viewpoint based on the study’s results. However, imagine someone coming up to you and saying “You have pneumonia; you’re now 200% more likely to die than before. By the way, given that awful news, would you rather be an additional 20% more likely to die or not?” Who would answer “Whatever, no great impact either way”? 20% doesn’t seem like much only because it’s being compared to 200%, but I’d definitely consider a 20% increase in number of deaths a significant impact.
Abstract, with link to full text for those with access: http://www.thelancet.com/journals/laninf/article/PIIS1473-3099%2810%2970258-9/abstract
ICT article: http://www.infectioncontroltoday.com/news/2010/12/resistance-does-not-greatly-impact-mortality-in-icu-patients-with-hais.aspx
Monday, December 6, 2010
Checklist at work - Rhode Island hospitals reduce BSI rates using the Checklist
Collaboration among Rhode Island hospitals' intensive care units (ICUs) to reduce infection rates led to significant reductions of central line-associated bloodstream infections (CLABSIs) and ventilator-associated pneumonia (VAP). The state's 11 acute-care hospitals formed The Rhode Island ICU Collaborative in 2005 with the goal of reducing infection rates in the hospitals' 23 ICUs. The effort was partially paid for by insurance companies and had strong backings of the state government.
The ICUs used the Checklist developed by Dr. Peter Pronovost's team at Johns Hopkins Hospital. By June 2010, the effort had saved 73 lives, avoided 3,271 patient days, and saved $11.5 million. Although the effort focused on ICUs, the same model is applicable to other units within the hospital.
Rhode Island Department of Health now publishes quality measures including infection rates on a public website.
Abstract and link to full text of the study is here.
Sunday, November 28, 2010
First large study in a decade finds little progress on patient safety in hospitals
Researchers from Brigham and Women’s Hospital undertook the largest study on patient safety since 1999. The results showed little progress on patient safety in hospitals. The study looked at cases of medical harm at ten hospitals in the State of North Carolina - a state that has shown a high level of engagement to improve patient safety relative to other states, as measured by the hospitals’ enrollment rates in national patient safety initiatives.
The study found 588 cases of medical harm for 10,415 patient-days or 25.1 injuries per 100 admissions. The top three causes of medical harm were procedures (186), medications (162), and hospital acquired infections (87). Patients in 42.7% of the cases required extra time in the hospital, 2.9% of the cases resulted in permanent injury, and 2.4% of the cases contributed to patient death.
One interpretation of the study results is that, in spite of years of efforts to improve patient safety, evidence-based safety practices are still rare in practice. Some hospitals have made significant strides in certain areas of care, such as in the adoption of electronic medical records and computerized physician ordering systems, but these improvements are often made independently of other areas, usually lacking coordination and an overarching strategy.
The last large scale study on patient safety was conducted in 1999 by the Institute of Medicine. The results of that study brought patient safety into the national spotlight. Results from this new study will hopefully lead to more concerted efforts to reduce medical harm through better utilization of resources, collaboration, and adoption of evidence-based practices.
Full text of the study in the New England Journal of Medicine
Tuesday, November 23, 2010
A Holistic Approach to Managing Urinary Catheterization
Although the article in Healthcare Informatics is titled “Intervening on Preventable Infections with IT,” it’s a whole lot more than IT. The article addresses using an EMR system to either remind a nurse to check if a urinary catheter should still be in place, or to place an automatic stop order by default. The clinician can only override the stop order when the patient meets specific criteria to leave the catheter in place.
Dr. Jennifer Meddings of the University of Michigan Health System digs deeper and describes the solution more broadly. In addition to alerts and automatic stop orders, the solution requires the political empowerment of nurses to issue stop orders, strong considerations for usability and workflow in the system, and understanding the root causes for clinicians to place urinary catheters in the first place.
One problem area is with regards to who receives alerts. Sometimes, alerts are produced in an EMR system and not delivered to appropriate decision makers or those responsible for catheter placement. The article also mentions combining high-tech solutions with low-tech, such as attaching a sticker to a catheter bag requiring the person placing the bag to indicate the specific reason for placing the catheter.
These issues serve as a great reminder that technology is never a panacea and that whole solutions for infection prevention need to take into consideration people, process, and technology.
Healthcare Informatics: Intervening on Preventable Infections with IT
Monday, November 22, 2010
CDC considers rule change for pricing of antibiotics
The annual number of antibiotics introduced to the market has been falling around the world. Between 2003 and 2007, only 5 new antibiotics were approved by the FDA in the US. In an effort to encourage the research and development of new antibiotics, the CDC launched a campaign on November 15th to stop the overuse of antibiotics. Key to the campaign is a proposed change in the pricing of these medicines. Currently, pharmaceutical companies have little incentive to develop new antibiotics because new antibiotics are likely to be used only sparingly at first in order to stave off the emergence of resistance. Conservative use of new antibiotics means less profit for the pharmaceutical company, which means it is unlikely to recoup the upfront investment within the fixed patent protection period.
The new solution proposed by the CDC would compensate companies for the true value of the antibiotic. Under the new proposal, new antibiotics will no longer be subjected to the traditional patent period; instead, payment for new antibiotics would be conditioned on meeting conservation and resistance targets set by the CDC. One example could be the rate of emerging resistance. If the company's antibiotic meets the target then it would maintain its market exclusivity. The government hopes that the proposed plan will give incentive to drug companies to develop new antibiotics under the new proposal.
The development of new antibiotics is important because there is an overwhelming number of outbreaks of hospital acquired infections, like MRSA, which could be controlled and treated with these drugs. Among the other diseases that could be targeted by new antibiotics are malaria, anthrax, and tularemia.
New York Times article
Boston Global article
Tuesday, November 16, 2010
A song on best infection prevention practices
Ron uses his singing talent to teaching others about good infection prevention practices.
Monday, November 15, 2010
State of HAIs in Canada
I recently read that the Women’s College Hospital in Toronto has banned magazines in patient waiting rooms in an effort to control the spread of germs (Article). Then over the weekend, it was announced that the Peterborough Regional Health Centre stopped admitting patients to one of its units because of an “uncommon” outbreak of C. diff., MRSA, and VRE (Article). Looks like our neighbor up north are having bad luck with infections.
Canada has ~200,000 HAIs per year, of which 8,000 result in death. An article published in April of this year found that the overall incidence of both MRSA colonization and MRSA infection increased 17-times in Canadian hospitals from 1995-2007 (Article).
A study published in 2003 concluded that infection control departments in Canada are significantly under resourced. Of the 172 hospitals surveyed in the study, 42% of the hospitals had fewer than 1 infection preventionist (IP) per 250 beds (the average in the U.S. is ~ 1 IP per 150 beds). The chart below shows how Canadian IPs were spending their time during the survey period. You can compare these percentages to those of U.S. IPs in an earlier post.
| Activity | % of IP Time |
| Surveillance | 30% |
| Teaching infection control to others | 14% |
| Writing or reviewing policies | 12% |
| Attending meetings | 11% |
| Managing epidemics/outbreaks | 8% |
| Regional infection control activities | 6% |
| Evaluation of products | 5% |
| Other (Consultations, construction, clerical, research) | 14% |
Tuesday, November 2, 2010
Scientists confirm the roots of Europe’s plagues
Separate teams of scientists studying the origins of Europe’s historical plagues confirmed in a study published last week that the plagues were caused by bacterium Yersinia pestis.
Europe experienced three great plagues in its history, the Justinian Plague in the 6th century, the Black Death from 1347 to 1349, and the Great Plague of London from 1665 to 1666. Amongst the three, the Black Death was the deadliest and is estimated to have killed 30%-60% of Europe’s population. The Great Plague of London killed an estimated 100,000 people (~20% of London’s population), and the Justinian plague, which was the first great plague, struck the Byzantine Empire from 541 to 542 AD, killing around 100 million people.
The three plagues were caused by three different strains of the bacterium Yersinia pestis. By comparing the genetic makeup of the bacteria from mass burial grounds across Europe in which the dead were interred to the genetic variations in living strains of Yersinia pestis, scientists conclude that the three strains shared a common ancestor and most likely originated from China. However, the killing of humans by Yersinia pestis is likely an "accident" as scientists believe that the natural hosts of the bacterium are various species of rodents, and that it has no interest in people.
This map shows how the bacterium might have spread from China to the rest of the world
New York Times Article on the Great Plagues
Monday, November 1, 2010
Illinois Hospital Association launches new campaign to combat HAIs
The Illinois Hospital Association, representing over 200 hospitals in the state of Illinois, launched the "Raising the Bar" campaign last week through the newly established Quality Care Institute (QCI). This new campaign has several objectives including:
QCI hopes to make Illinois a national leader in quality care and patient safety
- Reduce 30-day hospital readmission rates for congestive heart failure, heart attack, and pneumonia.
- Reduce hospital-acquired conditions and infections such as MRSA, C Diff, CLABSI, CAUTI, SSI, and deep vein thrombosis and pulmonary embolism following certain orthopedic procedures.
QCI hopes to make Illinois a national leader in quality care and patient safety
Friday, October 29, 2010
India restricts antibiotic use in light of NDM-1
The Indian Union Health Ministry announced this week that it is planning to tighten control of antibiotic use. Certain antibiotics, such as carbapenem, imipenem, and meropenem, will be put under more stringent restrictions if the new rule is passed. Other ideas under consideration are mandatory “drug control” and “infection control” committees in hospitals, where the drug control committee will oversee the use of controlled antibiotics and the infection control committee will monitor and analyze infection rates.
The proposed changes are aimed to combat the spread of NDM-1 superbug and to slow the evolution of other drug resistance bugs in the future. NDM-1 superbugs are resistant to most antibiotics; in fact, the prevalent use of antibiotics in India India in August of this year and has quickly spread to other countries, including the U.S.
Wednesday, October 27, 2010
Drug resistant Klebsiella a growing problem for the Chicago area

The challenge for Chicago hospitals and nursing homes now is to contain the spread of KPC bacteria. Early identification of patients who may be carriers is key, as well as better communication between different facilities when a patient colonized with KPC bacteria is transferred from one to another.
Links to relevant articles:
IDSA article on KPC cases in metropolitan areas
Chicago Tribune article on KPC cases in the Chicago area
Tuesday, October 26, 2010
"In trying so hard to contain the infection, had we lost sight of the person?"
Dr. Pauline Chen asks this question in her article, "Losing Touch with the Patient," which was published in last week's New York Time (October 21, 2010). The story Dr. Chen tells is one of the patients for which she helped care, a man with an infection from a multi-drug resistant organism and who spent the last few weeks of his life in contact isolation. Dr. Chen observed the patient's emotional shift during contact isolation - as healthcare workers' visits became infrequent and less interactive due to isolation precautions, the patient withdrew emotionally.
Contact isolation is meant to prevent the spread of infections. Previous researches have shown that patients in contact isolation receive lower quality of care and are more dissatisfied with their care. The question, therefore, is how hospitals can best balance the interest of individual patients to the patient population at large.
Links to contact isolation research:
Safety of Patients Isolated for Infection Control
Ethical Implications of Active Surveillance Cultures and Contact Precautions for Controlling Multidrug Resistant Organisms in the Hospital Setting
Monday, October 25, 2010
Arizona uses video competition to educate public about infection prevention
In the spirit of International Infection Prevention Week (last week), the Arizona Department of Public Health launched a video contest to educate the public about infection prevention.
According to one news source, The East Valley Tribune, hospital-acquired infections kill 2,000 people in Arizona each year, which is higher than the number of people killed in car accidents. Arizona is currently not considering public reporting of HAIs and is instead focusing on basic preventative measures such as hand hygiene and central line insertion practices.
According to one news source, The East Valley Tribune, hospital-acquired infections kill 2,000 people in Arizona each year, which is higher than the number of people killed in car accidents. Arizona is currently not considering public reporting of HAIs and is instead focusing on basic preventative measures such as hand hygiene and central line insertion practices.
Saturday, October 23, 2010
Interview with iScrub Lite developer Chris Hlady

iScrub Lite, a free iPhone/iPad app for recording hand hygiene observations, is making a lot of buzz in the infection prevention community since its launch over a year ago. I recently chatted with one of the app’s developers, Chris Hlady, to learn the story behind iScrub Lite.
EP: Could you describe what iScrub Lite does?
CH: iScrub Lite is an iPhone/iPad app for hand hygiene observers to record their observations. Hand hygiene observers are often infection preventionists, they measure hand hygiene compliance by watching healthcare workers (HCWs) go in and out of patient rooms and see if the HCWs are properly washing their hands both before entering and after leaving a patient’s room.
EP: Where did the idea for iScrub come from?
CH: It’s been over 2 years since the original conception, so I may not recall all the details. Basically when Apple first announced the App Store, I felt that it was going to become a very important platform. I began working on a game for the iPhone in order to learn how the platform worked. My advisor, Dr. Phil Polgreen, who is an epidemiologist at the University of Iowa, was very interested in hand hygiene and he gave me the idea for an app for hand hygiene.
We demoed a prototype at the local Iowa APIC conference in 2009 and got positive feedback from the nurses there. That experience encouraged us to move forward with the concept.
EP: What were some key considerations in the design process?
CH: We wanted the app to be simple and very easy to use. We saw that many hospitals were using paper forms to record their observations, and their processes sometimes required multiple forms.
We wanted to create a standard that improves the existing process.
Another goal for iScrub Lite was to cut down the feedback period. We found that in many cases observations were not communicated until weeks or even months later. We wanted to create a tool that lets nurses get results sooner and enables faster communication to HCWs.
EP: How many iScrub users are there?
CH: 3,000 users have downloaded iScrub Lite in the last 6 months.
EP: What kind of feedback have you been getting?
CH: We have been getting a lot of feedback. A lot of people are asking for iScrub Lite for the Blackberry and Android. We also get a lot of inquiries for iScrub Pro.
EP: What’s going to be in the Pro version?
CH: In the Pro version our main goal is to make it easier for nurses to make observations on a large scale. We also want to make reporting easier so that it will enable benchmarking. For example, a hospital can benchmark compliance among units in the same hospital or against other hospitals.
EP: What was the most surprising thing you learned during the making of iScrub Lite?
CH: How many different ways hospitals are doing hand hygiene observation. There are a lot of inconsistencies and disagreements over hand hygiene policies and practices.
Chris Hlady is a graduate student in the Department of Computer Science at the University of Iowa. Fellow graduate students and CompEpi research group members Donald Curtis and Jason Fries are also developers on the iScrub team.
Wednesday, October 20, 2010
Big pharma make big bets on infectious diseases: J&J and Glaxo invest in treatments for infectious diseases
Infectious diseases are catching the attention of big pharmaceutical companies lately. Over five years ago, GlaxoSmithKline started investing in flu vaccines with the anticipation that new variants of flu viruses are emerging and will cause global pandemics. Glaxo began delivering its new H1N1 vaccine last week and has already received over 440 million orders from governments around the globe.
Another pharmaceutical giant, Johnson & Johnson (J&J), recently acquired Crucell, a Dutch vaccine producer, for $2.42 billion. The acquisition is a strategic move that positions J&J in the vaccine market. J&J also announced that it plans to expand its research to encompass infectious diseases like HIV and hepatitis C.
Vaccines are more difficult to make and require larger upfront investment than prescription drugs. So, as patents for brand-name drugs expire and margins fall, big pharma companies are looking to produce vaccines to bolster a business that is less likely to be undercut by low-cost producers.
Tuesday, October 19, 2010
Variations in CLABSI surveillance
At a recent client meeting, an infection preventionist asked how to ensure consistency in infection reporting among hospitals, considering infection rates will soon be published on CDC's Hospital Compare website. I am not sure anyone has an answer to her question, but given the recent study results published on CLABSI surveillance, there exist large variations in how hospitals measure and report CLABSI rates. The study suggests that a lot of work remains to be done to ensure consistency and validity in how hospitals conduct CLABSI surveillance.
Here are some of the findings from the study, which was published in the October issue of the American Journal for Infection Control (AJIC):
Here are some of the findings from the study, which was published in the October issue of the American Journal for Infection Control (AJIC):
- 100% of the infection control departments reported inclusion or exclusion of central line types inconsistent with the CDC CA-BSI definition
- 50% calculated line-days inconsistently
- Only 50% used a strict, written policy for classifying BSIs
- Though more than 80% of the hospitals surveyed reported having a formal, written policy about obtaining blood cultures, less than 80% of these address obtaining samples from patients with central venous lines, and any such policies are reportedly followed less than half of the time
- Substantial variation exists in blood culturing practices, such as temperature thresholds, preemptive antipyretics, and blood sampling (volume, number, sites, frequency).
Monday, October 18, 2010
This Week is Infection Prevention Week!
This week is the International Infection Prevention Week and this year's theme is "Infection prevention is everyone's business." The Association of Infection Prevention (APIC) is sponsoring a number of webinars on infection prevention starting today.
Link to APIC's list of events for this week is here
Link to APIC's list of events for this week is here
Magic Number 7
Here is a question for you: For how many days were you asked to take your last antibiotic prescription? Was it 7 days? If so, have you thought of why?
Sunday's New York Times (October 17th) featured an insightful as well as worrisome opinion piece on why antibiotics are almost always prescribed for 7 days, as opposed to any other number. It turns out that there is really no scientific basis for the number 7. It's simply a convention and a habit. In fact, the author of the article points to a research study that shows that in the case of uncomplicated pneumonia, taking antibiotics for 3 days is as effective as the recommended 7 days.
The author then smartly points out that by having people take more pills than necessary, the overdose not only contributes to rising healthcare costs, but also to the evolution of antibiotic-resistant superbugs.
Here is my simple calculation:
If 3 days of antibiotics is as effective as 7 days, then a person will be taking 4 more pills than necessary (assuming he/she is taking one pill per day). That's more than double the necessary dosage. Translate this to the entire U.S. population, this means that at any given time, there are twice as many antibiotics taken than necessary!
New York Times article here
Research study on the effectiveness of antibiotic treatment here
Thursday, October 7, 2010
Germ fighting superheros roam New York City streets

The Association of Professionals for Infection Control (APIC) teamed up with Alliance for Consumer Education (ACE) to launch a new hand hygiene education using two superheros. Ace Clean and Iron Man demonstrated proper hand washing techniques in New York City's Times Square on October 1st.
Video link for the superheros is here
Wednesday, October 6, 2010
Long journey for electronic medical record adoption
The Sunday's edition of The New York Times (10/3/2010) has a story on the journey of Doerr Brother's healthcare software company. The story exemplifies the challenges facing many technology companies that service the American healthcare industry.
John and Tom Doerr started ClearPractice in 1999, a software company that made electronic health record products for small physician practices. The brothers thought that the obvious benefits of EHRs would make their software an easy sell. However, 10 years into the business, they had fewer than 500 doctors using the product. Since 2000, many large health systems have adopted EHRs but adoption among small physician practices is still lagging.
Small physician practices provide more than 85% of the healthcare services offered in the U.S. Almost all physicians operate on a fee-for-service model, which means the incentive is to do more of everything - tests, prescriptions, surgeries, etc. - but no incentive to adopt EHRs. The federal stimulus package will reduce the cost for adopting EHRs through subsidies; however, a fundamental shift in healthcare economics is needed in order to drive the adoption of EHRs among small physician practices.
Hospitals have historically viewed infection prevention as a heavy expense. The same rationale that prevents small physician practices from adopting EHRs, i.e. high investment cost and lack of quantifiable benefits, also prevents hospitals from adopting best practices and new technologies for infection prevention. Mandatory reporting and pay-for-performance are pressuring hospitals to scrutinize their infection rates more closely, which will hopefully drive up adoption of new technologies and best practices
Times' article on Doerr Brothers
Monday, October 4, 2010
Interview with creator of the board game Pandemic

Pandemic is a board game in which players cooperate to control outbreaks and eradicate disease. It’s played almost on a weekly basis at Vecna by a multi-disciplinary team of employees including software engineers, clinicians, systems administrators, project managers, and attorneys. It’s a unique game in that no single person wins; the team either wins together or loses together.
Board Game Geek: Pandemic Page
I had a chance to interview Pandemic’s creator Matthew Leacock this past Wednesday. Matthew formerly worked as a UI specialist for Yahoo and is now part of a new venture called Sococo. He designs board games on his spare time. He generously gave his time to answer a few questions:
R: What was your inspiration for Pandemic?
M: Classic board games like Monopoly are notorious for allowing an individual player to dominate the entire game while everybody else watches as they get screwed over. “Euro-games” or German board games are shorter and keep players involved and engaged. If you’re eliminated, you don’t have to wait too long to play again. If it’s not your turn, you’re still engaged with the game.
Co-op games like Lord of the Rings really broke it out for me. It wasn’t a kids’ board game where outcomes were randomly determined. Lord of the Rings also introduced the notion of self-sacrifice where you could perform an action that benefitted the team but didn’t necessarily help you out.
R: How did you decide on the theme for Pandemic?
M: The choice of subject matter was a natural fit. In Lord of the Rings, the villain is Sauron who feels un-human and has an emergent behavior like a disease. When you design a game with that kind of opponent, you have to create a paper algorithm that describes how the opponent emerges, how it spreads, and its impact on the players. For Pandemic, I had to define the mechanics of the outbreaks. I also designed a game in my youth about chain reactions from a nuclear reactor with similar mechanics. Disease just naturally fit after that, and it didn’t hurt that SARS was in the news during that time.
R: How much did you rely on historic pandemics or movies about them?
M: I never saw Outbreak. I’m sure 12 Monkeys played into it a little bit. I still remember the scene where the bioterrorist is running through the security gate. I’m familiar with Andromeda Strain but that’s a bit of a stretch. Really, it was mostly because SARS was in the news.
R: What kind of subject matter expertise did you rely upon when designing the game?
M: I’ve done games in two different ways – starting with a theme and then defining the mechanics, or defining the mechanics first and crafting the theme later. It’s better to focus on the mechanics first. Put it together and make it feel right. I did play it with people who were knowledgeable about the subject matter to make sure I didn’t incorporate some huge gaffe. I considered an educational component where facts could be illustrated on cards – information about different diseases, and tips on prevention. I decided against it because it’d be too much information and too many cards.
R: Have you gotten feedback from epidemiologists or other people in public health?
M: I’ve gotten positive feedback from the CDC in Atlanta. They actually sell Pandemic in their gift store. Some epidemiologists, friends of friends mostly, have enjoyed the game. I’ll occasionally see blog posts on Boardgamegeek about somebody who’s in the industry who really enjoys the game.
R: The cooperation in Pandemic is noble. I feel real world cooperation isn’t so pure. In the SARS outbreak, for example, while WHO did a great job facilitating information sharing among researchers, many groups withheld information in the hopes of publishing before others did. Have you considered modeling that element?
M: There are a couple of cards in the Brink expansion that represent that kind of negative behavior. It was easier to design the game in the beginning when it was just the players against the disease. Having different incentives for the different roles just introduced too much complexity.
R: I know this game is making its rounds in the hi-tech community. Start-up founders and software company execs get together to play. Do you have hopes that this will be the next Settlers of Catan?
M: All of my hopes have been exceeded. It’s been translated into 12 languages and has sold over 100,000 copies. I’d be happy if people pointed to it and said that it’s a very fun, collaborative game.
Wednesday, September 29, 2010
Study finds correlation between electronic surveillance systems and IP satisfaction
A survey study published in this month's American Journal of Infection Control looked at the impact of electronic surveillance systems (ESS) on infection preventionists' (IPs) jobs. IPs from over 200 hospitals in California participated in the survey. One very interesting finding from the study is that IPs with ESS have more organizational support and that organizational support is highly correlated with IPs' satisfaction level.
The study also provides an informative look at the changing role of today's IPs. The table below summarizes how today's IPs spend their time:
Although the study finds that IPs with ESS don't necessarily spend less time on surveillance, they do allow the IPs to spend less time on data collection and more time on decision making and implementing preventative interventions.
Abstract and link to full text here
The study also provides an informative look at the changing role of today's IPs. The table below summarizes how today's IPs spend their time:

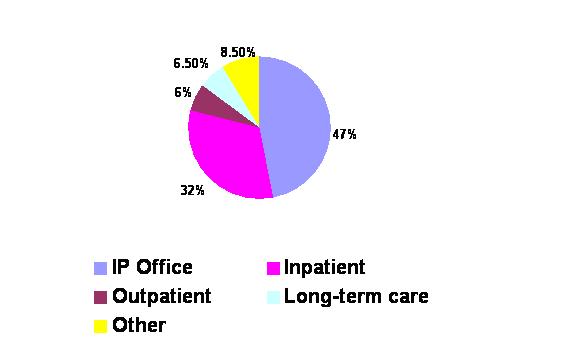
Abstract and link to full text here
Monday, September 27, 2010
Predicting Epidemics using Social Network Analysis

We posted a few months ago on the book Connected and how social network analysis is relevant to the fields of epidemiology and infection control. In the journal PLoS One, the authors Christakis and Fowler published specifics on the study briefly mentioned in Connected about a social network experiment performed on the campus of Harvard University.
Long story short, by mapping out the network of friends in a group of over 300 students, they were able to predict the onset of a flu epidemic two weeks earlier than through random sampling or by other means. In the case of SARS or swine flu, those two weeks could be the difference between a local epidemic and a global pandemic if public health officials had access to this data. There are many potential applications for social network analysis in the study of disease, but real-time public health applications may require private health data that individuals are as yet unwilling to make available outside of a controlled study on a college campus.
Big Think: A Better Way to Predict Epidemics
http://bigthink.com/ideas/24058
PLoS ONE: Social Network Sensors for Early Detection of Contagious Outbreaks
http://www.plosone.org/article/info:doi/10.1371/journal.pone.0012948
Big Think: Nicholas Christakis Interview
http://bigthink.com/nicholaschristakis
Thursday, September 23, 2010
New York State releases HAI report
Earlier this month, the New York State Department of Health released its 3rd annual report on hospital-acquired infections (HAIs). Some good news from the report:
1. Surgical site infection (SSI) rate in New York was 5.3 per 100 procedures, lower than the national average of 5.6 per 100 procedures and has been declining since 2007, when New York first started reporting HAIs.
2. Central line associated blood stream infection (CLABSI) rate has fallen 18% in the last two years.
3. The dollar savings associated with reduction in CLABSI rates in adults, pediatrics, and neonatal ICUs in New York was estimated to be between ~$2.5M and $10M.
One of the report's recommendations was that hospitals need to integrate health information technology systems to enhance infection prevention and reporting efforts.
Full Report Here
Tuesday, September 21, 2010
Using EMR data to determine origin of HAI
It's known that certain settings like healthcare, long-term care, and prison facilities increase the risk for certain infections. A prime example is MRSA. The challenge has been to determine where the patient acquired the infection, either from the community at large or from a healthcare facility. The distinction between the two is important for the monitoring, treatment, and prevention of infections.
A study by JS Wilson developed a process that identifies healthcare facilitiese from patients' addresses in the EMR database, automatically categorizes the address as either a healthcare facility or a residential address, and finally decides whether or not the infection is likely to be community or healthcare acquired.
This is an interesting attempt to use EMR data in assessing infection risk and opens the door to further investigating the effects of social networking on infections.
Full research paper here
Thursday, September 16, 2010
Book Review: Best Care Anywhere

Philip Longman’s second edition of Best Care Anywhere is a valuable, high level summary of the history of the Department of Veterans Affairs, the story of the VistA EHR system, and how incentives can be aligned within this huge health care system to achieve some of the highest scores on quality metrics, including HAI rates.
Of particular interest to me was the story of how the VistA EHR system was originally created. VistA was the brainchild of a community of computer-savvy VA physicians, and was developed in occasional opposition to the wishes of senior leadership. A virtual “Underground Railroad” emerged to enable the continued development of the system through the 1970’s and 1980’s. VistA has become legitimate during that time, with support from several presidential administrations, and adoption beyond the VA. It's interesting that earlier this week, an RFI has been released seeking assistance in maintaining the open source nature of VistA to continue this legacy.
Longman proposes a controversial strategy of extending the VA’s model of health care delivery beyond the VA, asserting that such an approach would improve care quality and reduce health care costs. He proposes not only extending VA's reach by opening access to non-veteran beneficiaries, but also implementations of VistA well beyond the VA into community and rural hospitals.
I'm very curious to see the response of policy makers, providers, and patients towards this controversial new strategy of health care quality transformation.
Tuesday, September 14, 2010
NDM-1 found in Massachusetts
Back in August, NDM-1 bacteria made national news when it was discovered in Europe and many predicted that it will spread to the rest of the world. Yesterday, I read on Boston Globe's online portal that a case of NDM-1 had been found in Massachusetts General Hospital (MGH).
 NDM-1 is a gene that makes bacteria highly resistant to many classes of antibiotics. The bacteria originated in India, where unregulated use of antibiotics is common. The MGH patient had recently traveled to India, had spent time in a hospital there, and was undergoing cancer treatment at MGH when the bug was discovered. Two other cases have also been identified in California and in Illinois.
The most worrisome aspect of this bug is the lack of antibiotics to treat it. Currently, only two antibiotics are some what effective against NDM-1 bacteria: colistin and tigecycline, and doctors don't foresee any new antibiotics being developed in the near future. To quote the author of the article, "The paucity of drugs reflects not only the strength of the superbug but also the long-neglected development of new antibiotics."
Full text of the Boston Globe article
Monday, September 13, 2010
Twenty-First Century Plague: The Story of SARS
 During a recent visit to Toronto hospitals, I learned firsthand how the SARS outbreak affected infection prevention departments specifically and health care workers in general. I decided to do some background research on the outbreak and picked up Thomas Abraham’s Twenty-First Century Plague: The Story of SARS. It’s a quick read at 176 pages and takes the reader from SARS’ origins in southern China, tracking the disease step-by-step as it emerges in major cities, spreads internationally, and is eventually thwarted by the efforts of the global health community led by the World Health Organization. Some highlights include: the unusual transmission of SARS via bathroom drains and apartment building plumbing, how health care workers risked and lost their lives to control infections, and how network-enabled collaboration helped spread successful prevention strategies just in time.
It’s a must read for anybody curious about this recent global outbreak, and it serves as a harrowing reminder of how chaotic, confusing, and destructive a modern pandemic can be.
Wednesday, September 8, 2010
What's better for your health, "long ties" or "dense cluster?
Lately, there has been a lot of buzz on using social networks to change
health behavior.  Ron blogged earlier about Nicholas Christakis' book
Connected, this week a new research study came of out of MIT that shows that when it
comes to changing health behavior, having fewer friends that one knows
really well is better than having many friends whom one doesn't know well.

Professor Damon Centola from the MIT Sloan School of Management tracked
the number of people who registered for a health forum from two distinct
social networks.  In one social network, participants had "long ties" with
each other, meaning each participant knew many different people but didn't
know them well.  In the other social network, participants formed "dense
clusters," meaning each of them knew fewer people but knew them very well.

The study result showed 54% of the people from the dense clusters network
registered for the health forum and 38% from long ties network did.  This
study suggests that policies may be more effective when aimed at
communities and groups that act as clustered networks.

More about Professor Centola's study
Tuesday, September 7, 2010
Benefits and harms of patient isolation
There was a great essay written by Dr. Abigail Zugar on the topic of patient isolation in the New York Times.
Full text
Full text
Tuesday, August 31, 2010
HAI related provisions in the new health care reform bill
There has been a lot of buzz (and confusion) about the 1,000-page long health care reform bill that was signed into law in March by President Obama. Over the weekend, I challenged myself to read the entire bill and after failing to make it past the Table of Contents, I decided to read only the parts relevant to the prevention of HAIs.
The bill has several provisions on the public reporting of HAIs. Below is a summary:
The bill has several provisions on the public reporting of HAIs. Below is a summary:
- Beginning in October 2012, non rural-acute care hospitals that meet or exceed federal performance standards for at least five measures, including certain HAIs, will receive higher Medicare payments [HR 3590, Title III, Subtitle A, Sec 3001, p. 235]
- Beginning in October 2012, hospitals with high readmission rates for patients, including readmissions due to HAIs, will have their Medicare payment reduced [HR3590, Title III, Subtitle A, Sec 3205, p.290]
- Beginning in 2014, the federal government will reduce Medicare payments by 1% for those hospitals in the top quartile for hospital-acquired conditions, including certain HAIs [HR 3590, Title III, Subtitle A, Sec 3008, p.258]
- Beginning in 2014, the U.S. Health and Human Services Department will report, on its Hospital Compare website, each hospital’s record for medical errors and infections involving Medicare patients [HR 3590, Title III, Subtitle A, Sec 3008, p.258]
On a side note, there is a funny YouTube video on health care executives’ response to the bill.
Monday, August 30, 2010
Not all patients with VRE need to be isolated
Findings recently published in Clinical Infectious Diseases indicate that not all strains of VRE require contact isolation, which might be seen as counterintuitive. However, Sutter et al. looked at records for a 9-year period from a bone marrow transplant unit where contact isolation was not required for patients with VRE of genotype vanC – only for vanA and vanB.
All patients in the bone marrow transplant unit had routine rectal VRE screening and genotyping. Sutter et al’s goal was to estimate the risk of blood stream infections (BSIs) in patients colonized with VRE vanC. During the years from January 2008 to July 2008, only one case of BSI was detected, while 290 isolates of VRE vanC were obtained from 273 patients. This means that only 0.4% of the patients who had VREvanC developed a BSI, despite there being no contact isolation precautions in place.
Sutter et al. conclude that the study provides strong evidence that carriers of VRE vanC do not require contact isolation. If there isn’t a high prevalence of VRE vanC in your hospital, this might not be as useful, but if genotyping is done and vanC is detected, the hospital does not need to spend resources on contact isolation, and patient care is improved.
Article here: http://www.journals.uchicago.edu/doi/abs/10.1086/655824
New Technologies
We’re seeing all sorts of advances in fighting MRSA lately! AdvanSource Biomaterials Corporation recently received a patent for antimicrobial polyurethane resins, which can be used structurally or as coatings in different kinds of catheters, and are intended to help combat methicilin-resistant staphylococcus aureus (MRSA) infections.
Press release here: http://phx.corporate-ir.net/phoenix.zhtml?c=68271&p=irol-newsArticle&ID=1463328
Also, on the heels of the emergence of the NDM-1 gene, BioScience Laboratories announced that they’ve obtained seven clinical isolates of Carbapenem-Resistant (CR) Klebsiella pneumonia and Escherichia coli. BioScience Laboratories intends to use these isolates to test products for their predicted efficacy against bacteria containing the NDM-1 gene.
Press release here: http://www.24-7pressrelease.com/press-release-rss/bioscience-laboratories-announces-testing-capabilities-for-ndm1-165887.php
Octagam lots recalled
Market withdrawal of select Octagam 5% liquid preparation lots was initiated on August 20, due to an increased number of reported thromboembolic events, some of which were serious. Octagam is used to treat primary immunodeficiency diseases. The FDA advises customes not to administer any product from the lots being withdrawn.
See which lots were withdrawn, and read the full recall here: http://www.fda.gov/BiologicsBloodVaccines/SafetyAvailability/Recalls/ucm223897.htm
See which lots were withdrawn, and read the full recall here: http://www.fda.gov/BiologicsBloodVaccines/SafetyAvailability/Recalls/ucm223897.htm
Tuesday, August 24, 2010
New Hampshire releases first report on infections
Last week, New Hampshire released its first report on hospital-associated infection (HAI) rates. The report showed 134 infections during 2009, better than the 180 that was expected by state officials and lower compared to national data. Of the total 134 HAIs that were reported, 110 were surgical site infections (SSIs) and 24 were central line-associated bloodstream infections (CLABSIs).
New Hampshire passed the law in 2006 to publicly report hospital infection rates. In January 2009, all acute care hospitals began reporting CLABSIs and SSIs to the New Hampshire Department of Health and Human Services (DHHS). New Hampshire is one of 27 states that requires public reporting of hospital infections and is one of 20 states that have produced reports.
Monday, August 23, 2010
New coating kills MRSA on contact
Researchers have developed a way to coat surfaces with an enzyme that kills MRSA within 20 minutes of contact, says a recent publication in ACS Nano. The enzyme, lysostaphin, degrades cell walls of Staphylococcus aureus and epidermidis, thus killing the harmful bacteria.
The researchers had spent several years studying carbon nanotube-enzyme pairs, called conjugates. Enzymes in coating alone either degrade or leach into the surroundings, but when paired with carbon nanotubes, the authors found that the enzymes were more stable and more densely packed when embedded into polymers such as paint.
Lysostaphin is extremely selective, killing just S. aureus and epidermidis, is harmless to humans, and does not induce bacterial resistance. The enzyme-nanotube conjugate also doesn’t become clogged over time, a common problem with other antimicrobial coatings. Perhaps most impressively, antimicrobial films made with the conjugate were greater than 99% effective in killing all MRSA that came in contact with the film, measured after 2 hours. And there’s even more: the films are reusable and washable, and stable under dry storage conditions for at least a month.
The lysostaphin-nanotube conjugate could be embedded into paint used in hospital rooms, or into films to put on various other hospital surfaces. It will be extremely exciting to see how this technology is put to use.
Link to ACS Nano abstract: http://pubs.acs.org/doi/full/10.1021/nn100932t
Friday, August 20, 2010
HAI Reporting Survey
As you’re probably aware, the Centers for Medicare and Medicaid Services (CMS) recently released a rule that details HAI reporting requirements for Medicare-participating hospitals; starting January 1, 2011, hospitals will be required to report CLABSIs to NHSN, and they will be required to report SSIs starting January 2, 2012.
We would like to ask our readers where they are in the process of meeting the CMS HAI reporting requirement. We’ve developed a survey, and we would really appreciate it if you could take a few minutes of your time to complete it. It’s just 10 easy, multiple choice questions. We’ll publish the results once they’re compiled.
Please click here to take our survey!
Tuesday, August 17, 2010
You didn't really want that data, did you?
Missouri, one of the first states to pass legislation requiring hospitals to reveal annual HAI rates, has possibly deleted all their infection rate data collected from 2005-2008. State officials say that the data is too costly to maintain, and mention the sensitivity of the data as another motivating factor.
However, the law doesn’t explicitly give authority to the state health department to delete the infection data, or the associated tables and results produced from data analysis. The statute says “The data collected or published shall be available to the department”. Subsequent requests for the data by the St. Louis Post-Dispatch got conflicting answers; one state official said the data was deleted, another said that the data was available, just “not handy.”
The department later said it would take public requests for information, but they would only be honored if a programmer was available and only if the requester was willing to pay the retrieval costs. The state data manager, Mark Van Tuinen, cited budgetary constraints as the reason for data deletion, saying “Given our skimpy resources, we’re pretty much doing what the law tells us to do” – keep data compiled for a period of 12 months.
A note on the state health website says “Due to the sensitive nature of the data and limited resources, DHSS staff cannot provide data or records beyond what are displayed on this website.” Van Tuinen added, “Hospitals are sensitive about comparisons with each other.”
While it’s impossible to track the changes in infection rates without the data, it is interesting to note that the 2004 law establishing these reporting requirements did not allocate any funds with which to accomplish them. Missouri apparently had to face the question of how to keep the data accessible without any money to do it. Fortunately for the public, the St. Louis Area Business Health Coalition backed up the data each year before it was removed, so even if Missouri did delete the data, it does still exist.
Regardless of whether the data was actually deleted or not, the issue certainly raises questions about how states should frame and implement the laws that require them to report and store HAI data, and how to best serve the public while doing so.
St. Louis Post-Dispatch story: http://www.stltoday.com/business/article_9959b4e1-2634-5722-b21d-c32876d205a0.html
DHSS website with reporting note: http://www.dhss.mo.gov/HAI/definition.html
What's in a name?
Recent reports of a superbug from India named ‘New Delhi Metallo-beta-lactamase 1’ or NDM-1 are generating criticism from Indian leadership. Director General of Health Services R. K. Srivastava takes issue with naming the bug after the region and for its jab at antibiotics policy.
Srivastava "strongly refuted the naming of the enzyme as New Delhi metallo-beta-lactamase and also refuted that hospitals in India are not safe for treatment including medical tourism."
Medical tourism is growing in nations like India and Pakistan, and concern around a superbug specifically associated with the area could put the entire industry at risk. The UK Department of Health responded to the Lancet journal article by issuing an alert about the New Delhi superbug.
Controversy in naming diseases and organisms is not a new phenomenon; the World Health Organization (WHO) proceeded with caution in naming the SARS virus.
David Heymann of the WHO’s SARS team said, “We did not want to stigmatize particular areas, it could not be called Hong Kong Flu or Hanoi flu.” The WHO finally decided on the acronym SARS, which stands for “Severe Acute Respiratory Syndrome,” not realizing that “SARS” was similar to the common acronym SAR which is used to describe Hong Kong as the “Special Administrative Region.”
The problem also affects animals; naming diseases after animal species (e.g. bird flu, swine flu) can result in stigmatizing livestock, and result in their mass slaughter.
So, we’re left with letters and numbers. MBL-1, anyone?
Monday, August 16, 2010
Western eating habits: worse than you think?
A study recently published in Proceedings of the National Academy of Sciences indicates that a rural diet might protect children from inflammation and noninfectious colonic disease. Researchers compared the fecal microflora of 14 children ages 1-6 from a rural village in Burkina Faso to that of 15 similarly-aged children in Italy. The children from the village in Burkina Faso, Boulpon, consumed a traditional diet that is low in fat and animal protein, and high in starch and fiber, whereas the Italian children consumed a typically Western diet high in sugar, fat, animal protein, and starch, and low in fiber.
The two populations of children's gut microflora were similar while children were still being breast-fed; the differences grew once they started consuming the local diet. Di Filippo et al. found that the children from Boulpon had roughly twice as many Bacteroidetes species as the Italian children, and that the Italian children had roughly twice as many Firmicutes species as the children from Boulpon. A high ratio of Firmicutes to Bacteroidetes has been associated with obesity, potentially indicating that the Western diet of the Italian children predisposes them to future obesity.
The children from Boulpon also had a greater richness and biodiversity of gut microflora, including exclusive possession of a number of species that produce high quantities of short-chain fatty acids (SCFAs), which are known to protect against gut inflammation. As expected, the levels of SCFAs themselves in the Burkina Fasoian children were significantly higher than those in the Italian children. Additionally, though the Italian children were healthy, they had a significantly higher level of Enterobacteriaceae that are potentially pathogenic, like Shigella and Escherichia.
The results indicate that a Western diet could allow potentially harmful bacteria to gain a foothold in the gut, and could predispose children to obesity and gut inflammation.
Link to the article’s full text: http://www.pnas.org/content/early/2010/07/14/1005963107.full.pdf
Thursday, August 12, 2010
APIC and CDC to Provide Guidance on New CMS HAI Data-Reporting Mandate
The big news on July 30th, 2010 was that the Centers for Medicare and Medicaid services (CMS) enacted a rule requiring all Medicare participating hospitals to report data on central line associated bloodstream infections (CLABSIs) and surgical site infections (SSIs). Hospitals not submitting data on CLABSIs and SSIs may experience reduction in reimbursement payments.
APIC has taken the lead on providing information and guidance on the new reporting mandates with a webinar (details, link, and schedule still pending) in mid-August with speakers from CDC and CMS to discuss the reporting requirements. Additionally, both CMS and CDC are updating documents, support, and training.
HHS has also announced that its Hospital Compare web site will begin publicly reporting on infection rates among participating hospitals. Consumer Reports has similar data now, but Hospital Compare data can be expected to be more prevalent and current following the CMS rule and the 3,500 enrollments into the CDC’s NHSN program by Medicare participating hospitals.
Resources and information on CMS HAI Data-Reporting Rule:
CDC: New to NHSN? Page
APIC Statement on New CMS Rule
CDC Blog Posts on the CMS Rule
Text of CMS Rule
Wednesday, August 11, 2010
MRSA infections down, but new threat on the horizon
A study just published in The Journal of the American Medical Association (JAMA) shows that the incidence of hospital-onset methicillin-resistant staphylococcus aureus (MRSA) infection decreased by 28% from 2005 to 2008. The measurements, taken from 9 major metropolitan areas across the country, also show that MRSA rates for healthcare-associated community-onset infections decreased 17% over the same time period.
The study’s authors, Kallen et al., are unable to say why the rates decreased, but mention a couple possible factors. The first possibility is the widespread implementation of MRSA prevention practices. Kallen et al. note that “the fact that the observed reductions were greater among hospital-onset infections than healthcare–associated community-onset infections suggests that prevention practices in acute care settings contributed” to the decrease in MRSA infection rates. Another potential factor is a change in the strains associated with MRSA infections, but the authors state that there weren’t changes in MRSA strain composition during that time period, so this is unlikely to be a valid explanation.
Immediately on the heels of this good news comes a study published in The Lancet Infectious Diseases today, which details how a new bacterial gene might cause worldwide health problems.
NDM-1, which stands for New Dheli metallo-β-lactamase 1, makes bacteria highly resistant to many classes of antibiotics, including the carbapenems. Unfortunately, the gene has been determined to be readily transmitted and also highly adaptable. As bacteria that contains NDM-1 encounters bacteria that doesn’t, NDM-1 could insinuate itself into the new bacteria, thus creating a larger resistant population. The problem is particularly worrying because there is not a single antibiotic in the discovery and production process that is effective against NDM-1-containing bacteria – and because NDM-1 is highly adaptable, it could potentially change itself to resist any drugs that are developed.
In addition to this already grim news, most of the isolates taken from India were from community-acquired infections, which implies that bacteria with the NDM-1 gene are already pervasive. The NDM-1 gene has also already spread to the UK and Sweden – and some of the UK patients had recently traveled to India for medical treatments.
We’re left with a good news/bad news scenario: just as we are starting to see MRSA infection rates fall, we learn that NDM-1-containing bacteria is expected to spread around the globe.
JAMA article: http://jama.ama-assn.org/cgi/content/full/304/6/641
Lancet article: http://www.thelancet.com/journals/laninf/article/PIIS1473-3099%2810%2970143-2/fulltext
Subscribe to:
Posts (Atom)